
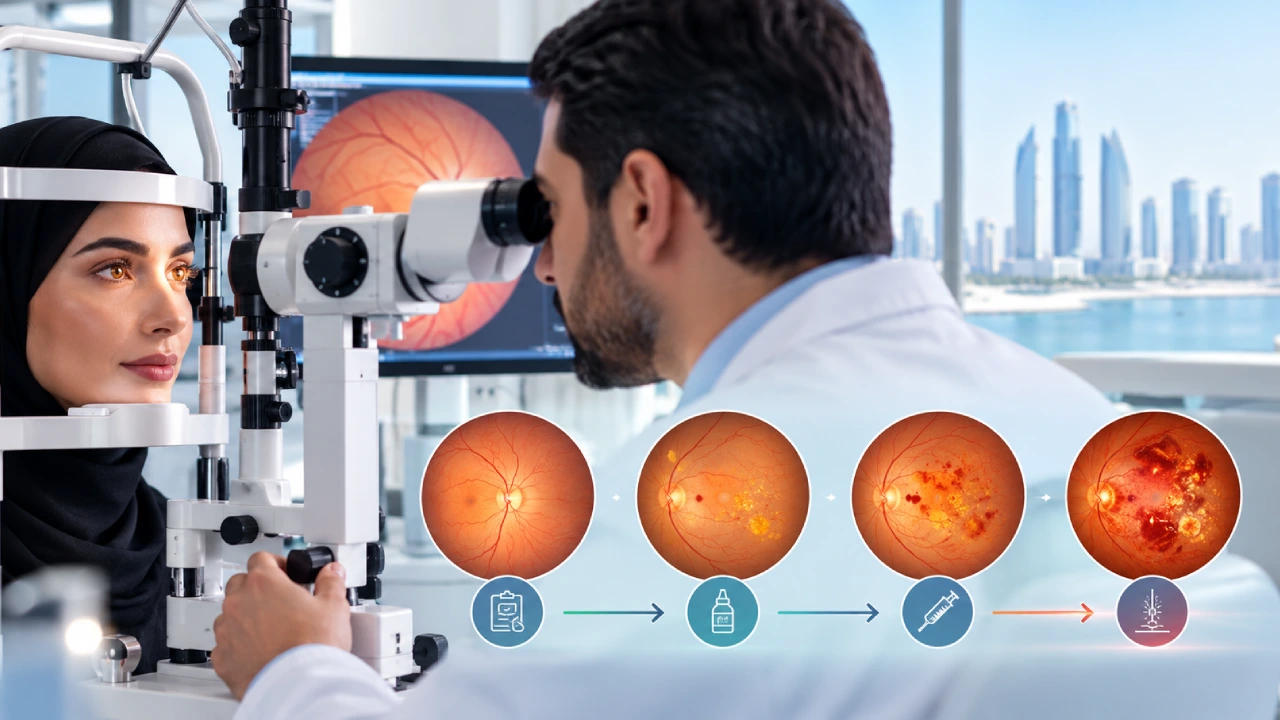
Diabetic retinopathy is a common form of diabetic eye disease and an important cause of vision impairment among people with diabetes. It develops when diabetes damages the tiny blood vessels in the retina, the light-sensitive tissue at the back of the eye.
Over time, eye damage from diabetes can cause retinal blood vessels to leak or become blocked. In advanced disease, abnormal new vessels may grow, increasing the risk of bleeding, scar formation and retinal detachment.
Treatment depends on the stage of the disease and any associated complications. Early changes may require monitoring and diabetes management, while more advanced disease may need injections, laser treatment or surgery. Regular examinations are essential because significant retinal changes can develop before symptoms appear.
Understanding the Stages of Diabetic Retinopathy
Proper staging helps retina specialists determine the most appropriate diabetic retinopathy treatment plan.
The disease is generally classified into four stages.
Mild Non-Proliferative Diabetic Retinopathy (NPDR)
Small retinal blood vessels develop tiny bulges called microaneurysms. Vision may remain unaffected, and patients often have no noticeable symptoms.
Moderate Non-Proliferative Diabetic Retinopathy
Blood vessel damage becomes more extensive, with additional bleeding, leakage or changes in retinal circulation.
Severe Non-Proliferative Diabetic Retinopathy
More extensive vascular damage and reduced retinal blood supply increase the risk of progression to proliferative disease.
Proliferative Diabetic Retinopathy (PDR)
Abnormal new blood vessels grow on the retina or optic disc. These fragile vessels can bleed into the vitreous, while associated scar tissue can pull on the retina and cause retinal detachment.
Diabetic macular edema can occur at any stage. It is assessed separately because swelling in the macula may require treatment even when retinopathy has not reached the proliferative stage.
Treatment for Early Stage: Mild Non-Proliferative Diabetic Retinopathy
Mild NPDR without diabetic macular edema usually does not require immediate injections, laser treatment or surgery. The focus is on monitoring retinal changes and managing diabetes and related risk factors.
Key strategies include:
- Working towards individual blood glucose and HbA1c targets.
- Managing blood pressure and cholesterol.
- Following an appropriate nutrition and physical activity plan.
- Taking prescribed medications consistently.
- Attending scheduled eye examinations.
When explaining diabetic retinopathy causes, it is important to consider both the duration of diabetes and long-term blood glucose exposure. Good diabetes management reduces risk but does not eliminate the need for screening.
Retinal examinations and imaging, when indicated, help specialists identify changes and adjust follow-up.
Treatment for Moderate Non-Proliferative Diabetic Retinopathy
Moderate disease generally requires closer monitoring to identify progression or associated macular edema.
Management may include:
- More frequent retinal examinations.
- Optical coherence tomography (OCT) when assessing macular swelling.
- Continued blood glucose, blood pressure and cholesterol management.
- Treatment of diabetic macular edema when clinically indicated.
Injections are not automatically required because retinopathy has reached the moderate stage. The decision depends on the retinal findings, visual function and associated complications.
Patients should report blurred or distorted vision, new floaters or other visual changes rather than waiting for their next scheduled appointment.
Treatment for Severe Non-Proliferative Diabetic Retinopathy
Severe NPDR carries a greater risk of progressing to proliferative diabetic retinopathy. Close specialist monitoring is therefore essential.
Treatment is individualized. Some patients continue with careful observation, while others may benefit from intervention based on their risk of progression, associated macular edema and ability to attend follow-up appointments.
Laser Treatment in Selected Cases
Panretinal photocoagulation may be considered for selected patients with severe NPDR to reduce the risk of sight-threatening progression.
Anti-VEGF Therapy When Appropriate
Anti-VEGF injections may be considered in selected circumstances and are commonly used when vision-impairing diabetic macular edema is present. They are not a routine requirement for every patient with severe NPDR.
The Role of Steroid Treatment
Steroid injections or implants may be appropriate for selected cases of diabetic macular edema. They should not be presented as standard treatment for severe NPDR alone. doi.org
The aim is to identify changes that need treatment before further eye damage from diabetes threatens vision.
Treatment for Proliferative Diabetic Retinopathy
Proliferative diabetic retinopathy is the most advanced stage in the standard disease classification.
Abnormal vessel growth, known as neovascularization, can lead to vitreous hemorrhage and scar tissue formation. Treatment aims to control this activity and reduce the risk of serious complications.
1. Laser Photocoagulation
Panretinal photocoagulation (PRP) is an established treatment for proliferative disease. It treats areas of the peripheral retina to reduce the signals driving abnormal vessel growth.
Treatment may require more than one session and aims to lower the risk of severe bleeding and vision loss.
2. Anti-VEGF Injections
Anti-VEGF medications suppress abnormal blood vessel activity. They may be used as an alternative to PRP in selected patients or alongside laser treatment.
Repeated injections and reliable follow-up may be necessary. The treatment plan takes account of associated macular edema, disease activity and the patient’s circumstances.
3. Vitrectomy Surgery
Advanced complications may require surgery rather than injections or laser alone. Vitrectomy allows the surgeon to remove blood-filled vitreous, release scar tissue pulling on the retina and perform additional retinal treatment where needed.
The decision depends on the nature and severity of the complication.
Advanced Complications: Vitreous Hemorrhage and Retinal Detachment
Vitreous hemorrhage and tractional retinal detachment are serious complications of proliferative disease. They are not separate stages in the usual four-stage classification, but they can substantially change the treatment required.
Vitreous Hemorrhage
Vitreous hemorrhage occurs when fragile abnormal vessels bleed into the gel inside the eye. Symptoms may include new floaters, a hazy or reddish view, or substantial loss of vision.
A retina specialist assesses the amount of bleeding and whether the retina remains attached. If blood obscures the view, an ultrasound examination may be needed.
Some episodes can be managed initially without surgery under close specialist supervision. Vitrectomy may be recommended when bleeding does not clear, repeatedly returns, prevents necessary retinal treatment or occurs alongside retinal detachment.
During surgery, the blood-filled vitreous is removed, allowing the surgeon to examine and treat the retina. Timing depends on the findings; patients should not wait for bleeding to clear without professional assessment.
Tractional Retinal Detachment
Scar tissue associated with proliferative retinopathy can contract and pull the retina away from its normal position. This is called tractional retinal detachment.
A detachment involving or threatening the macula generally requires vitrectomy surgery. The surgeon releases the traction by removing the tissue pulling on the retina and uses additional measures as required to support retinal reattachment.
A limited, stable detachment away from the macula may sometimes be monitored closely. A detachment that also involves a retinal tear may require more urgent intervention.
Anti-VEGF injections can have a supporting role in selected surgical cases, but they do not mechanically release established traction or reattach the retina.
Treatment for Diabetic Macular Edema (DME)
Diabetic macular edema occurs when leaking blood vessels cause fluid to accumulate in the macula, the central part of the retina responsible for detailed vision.
DME can occur at any stage of diabetic eye disease. Treatment depends on whether the center of the macula is involved, the effect on vision and imaging findings.
Anti-VEGF Injections
These are commonly the first-line treatment for center-involving DME that reduces visual acuity.
Steroid Injections or Implants
Steroid treatment may be considered when anti-VEGF therapy is unsuitable or provides an inadequate response. Eye pressure and cataract risk require monitoring.
Laser Therapy
Targeted laser treatment remains useful in selected cases, depending on the location and pattern of leakage.
Some patients with preserved vision may initially be monitored closely. Surgery may be considered when traction contributes to the swelling.
Role of Lifestyle and Systemic Control in Treatment
Eye procedures work alongside diabetes management. Controlling systemic risk factors remains important at every stage.
Blood Sugar Management
Agree individual blood glucose and HbA1c targets with your diabetes clinician. Consistent management can reduce the risk of progression.
Blood Pressure and Cholesterol Control
Managing blood pressure and cholesterol supports vascular health and forms part of comprehensive diabetes care.
Healthy Lifestyle Habits
Patients are encouraged to:
- Follow an appropriate, balanced diet.
- Maintain suitable physical activity.
- Avoid smoking.
- Take medications as prescribed.
- Attend both diabetes and eye-care appointments.
Coordination between ophthalmologists, endocrinologists and primary care physicians helps keep treatment aligned.
What to Expect During Treatment
Treatment schedules vary according to disease activity and response.
Patients receiving injections may need frequent visits initially, sometimes monthly, followed by an adjusted schedule. Reviews may include vision testing, a dilated retinal examination and OCT imaging.
Laser treatment is often performed as an outpatient procedure. Surgery involves a separate recovery plan and postoperative reviews. Your surgeon will explain any positioning, activity or travel restrictions relevant to the procedure.
Regular assessment allows retina specialists to adjust treatment. Continue attending appointments even when vision improves, because symptoms do not always reflect disease activity.
Risks and Complications of Treatment
The risks depend on the treatment and the condition of the eye.
Injection-Related Risks
Possible effects include temporary irritation, discomfort, a small surface bleed and changes in eye pressure. Infection inside the eye is uncommon but serious.
Steroid treatment can also increase the risk of cataract formation and raised eye pressure.
Laser Therapy Risks
Laser treatment may cause temporary blurred vision or discomfort. PRP can affect peripheral vision and night vision.
Surgical Risks
Vitrectomy may carry risks such as:
- Cataract development or progression.
- Further bleeding.
- Infection.
- Changes in eye pressure.
- Retinal tears or detachment.
- The need for additional surgery.
Increasing pain, redness or reduced vision after treatment requires urgent contact with the treating team.
Can Diabetic Retinopathy Be Prevented?
Not all cases can be prevented, but effective diabetes management can reduce the risk of developing or worsening retinopathy.
Protective measures include:
- Regular diabetic eye screening.
- Comprehensive eye examinations at the recommended interval.
- Blood glucose, blood pressure and cholesterol management.
- Appropriate nutrition, physical activity and smoking cessation.
Many patients need annual eye examinations, while established or progressing retinopathy may require more frequent reviews. Follow the schedule recommended by your eye-care team.
Understanding diabetic retinopathy causes helps patients manage risk, but screening remains necessary even when diabetes is well controlled.
When Should You See a Retina Specialist?
Arrange an assessment if you notice persistent blurred or distorted vision, dark spots or difficulty seeing at night.
Seek urgent eye care for sudden vision loss, a sudden increase in floaters, flashes of light or a curtain-like shadow across your vision. These symptoms may indicate vitreous hemorrhage or retinal detachment and should not wait for a routine appointment.
Conclusion
The management of diabetic eye disease depends on the stage, macular involvement and any complications. Early disease often requires monitoring and systemic control. More advanced disease may need injections or laser, while persistent vitreous hemorrhage and retinal detachment involving or threatening the macula may require surgery.
Timely diabetic retinopathy treatment, regular examinations and continued diabetes management can help preserve vision. Treatment may improve sight in some patients, but preventing further loss is often the main goal.
Schedule a comprehensive retinal evaluation at Bascom Palmer Eye Institute Abu Dhabi to discuss your retinal health, treatment options and follow-up needs.
Frequently Asked Questions
Can diabetic retinopathy be cured?
Treatment can control disease activity and reduce the risk of further vision loss, but it does not eliminate the underlying risk associated with diabetes. Injections, laser and surgery address different aspects of the disease. Some patients experience visual improvement, while others mainly achieve stabilization. Continued diabetes management and retinal follow-up remain important even after successful treatment.
How long does treatment take?
The duration varies with the stage, complications and response. Some patients require monitoring alone, while others need repeated injections or laser sessions over an extended period. Advanced complications may require surgery and postoperative care. Because retinopathy can become active again, long-term follow-up is usually needed even when an initial course of treatment is complete.
Are eye injections painful?
Numbing drops or local anesthetic are used to minimize discomfort. Patients may feel pressure or brief discomfort during the injection, followed by mild irritation or a gritty sensation. A small surface bleed can also occur. Significant or increasing pain, marked redness or worsening vision afterwards should be reported urgently rather than assumed to be a normal reaction.
What is the success rate of treatment?
There is no single success rate that applies to every stage and procedure. Outcomes depend on disease severity, retinal circulation, macular involvement and the extent of existing damage. Treatment may improve vision, stabilize it or reduce the risk of further loss. Your retina specialist can explain the expected goal and limitations for your eye.
Can vision be restored after treatment?
Vision may improve when macular swelling decreases or blood clears from the vitreous. However, longstanding retinal damage, poor blood supply or an advanced detachment may limit recovery. Surgery can address bleeding or traction without guaranteeing normal vision. Early assessment and appropriate treatment offer the best opportunity to preserve useful sight.